

For me or my family
Tutus, in Spanish: your checkup with samples taken at home or at a partner lab, your risk on five fronts and 20 minutes with a Corpus cardiologist. COP 350,000, all included.
Corpus AI is the primary care layer for Latinos around the world: it reads the clinical data that already exists, calculates each person's real risk of heart attack, stroke, hypertension, diabetes and chronic kidney disease, and tells the care team whom to see today. Validated in 382,589 Latin American patients and in 626,396 US adults, without retraining.

 HIPAA · GDPR · TRIPOD+AI
A real production deployment with a health-system partner in Latin America. Name withheld for confidentiality.
Tutus, in Spanish: your checkup with samples taken at home or at a partner lab, your risk on five fronts and 20 minutes with a Corpus cardiologist. COP 350,000, all included.
Insurers, providers and employers prioritize their population by real risk.
Each card links to the original piece, in Spanish.
 El emprendedor que busca predecir infartos con un algoritmo desarrollado por colombianos
 Corpus AI convierte una historia familiar en una apuesta para prevenir infartos
 Corpus AI: la startup colombiana que previno 467 infartos con IA
 Corpus AI: la compañía colombiana que utiliza inteligencia artificial para salvar vidas, “hemos contenido 467 infartos”
 Inteligencia artificial puede prevenir infartos en Colombia: no todo es crisis en salud
 Juan Felipe Forero: medicina predictiva e IA en saludCorpus AI: startup colombiana previene 200 infartos con IA y datos locales
 La compañía colombiana que utiliza inteligencia artificial para prevenir infartos, ACV y otras emergencias cardiovasculares
 Corpus AI busca prevenir infartos y ACV en la población
 Enfermedades crónicas concentran buena parte del gasto en salud y aumentan el reto para los sistemas sanitarios
They all run on the same calibrated risk engine, and each organization turns on the ones it needs.
Ranks the population by real risk and splits it into cohorts, each with its clinical action, from clinical data that is structured and standardized.
Appointment scheduling with reminders, transportation to the appointment and transcription of the visit into a structured note.
A care plan for each person, habit tracking and risk reassessment with every new data point, over WhatsApp.
The engine reads a population's clinical data and places each patient in one of four cohorts. Each cohort comes with its action: there is no score to interpret.
1,248,302 patients · 30-day window
Escalate · 24 h
8.2%102,361 patients
Contact · 7 d
17.9%223,446 patients
Care plan
33.6%419,429 patients
Passive follow-up
40.3%503,066 patients
A real production deployment with a health-system partner in Latin America. Name withheld for confidentiality.
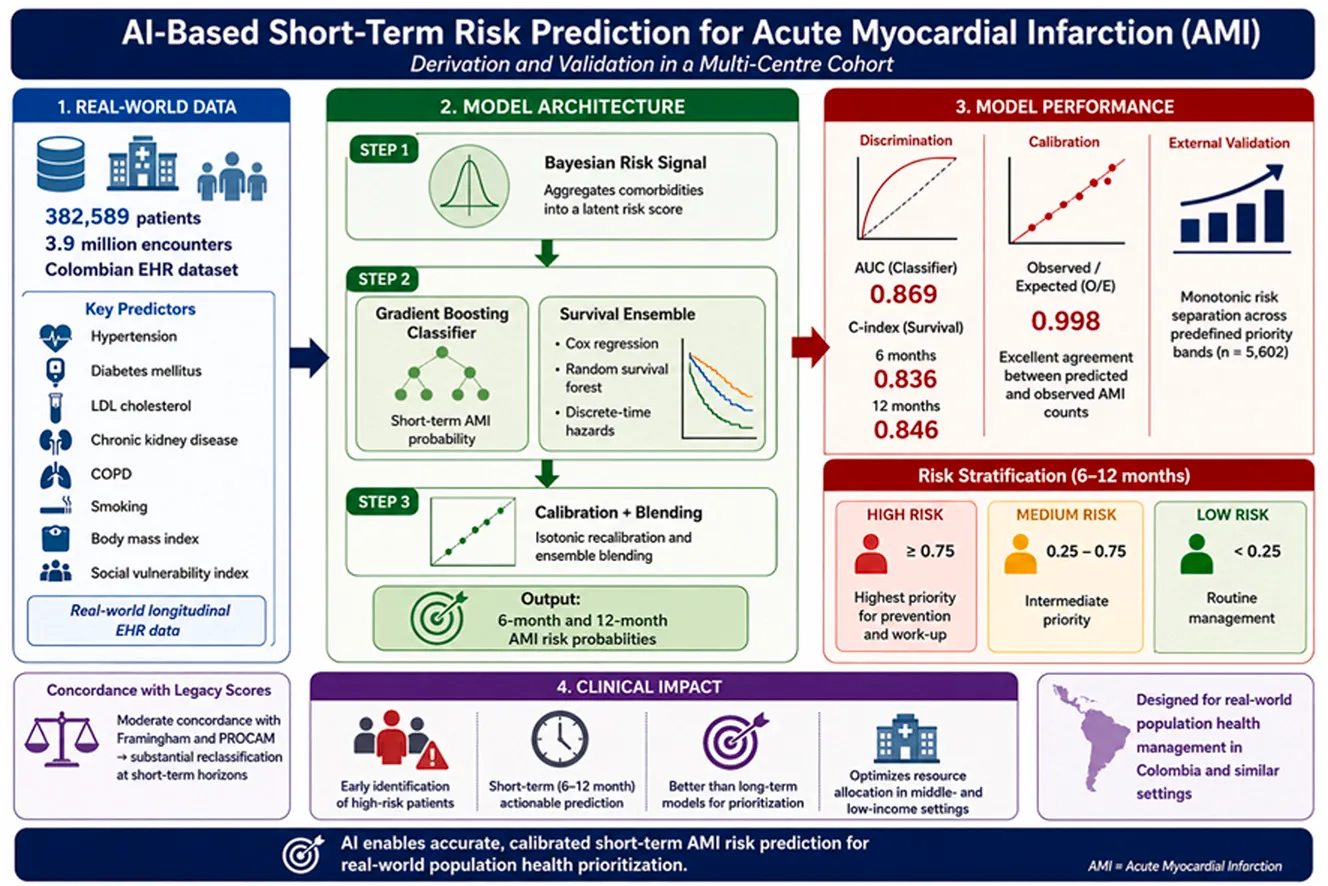
The model estimates the risk of a heart attack at 6 and 12 months from routine clinical data. It was derived and validated in an integrated cardiovascular cohort in Colombia; the open-access article is here in full.
Published article · IJCRP 2026
Amorocho-Morales JD, Parra Guevara S, Quintero-Muñoz E, Dimas G, Correa-Morales JE. Int J Cardiol Cardiovasc Risk Prev. 2026;30:200659. Published online on June 8, 2026.
© 2026 The Author(s). Published by Elsevier B.V. Open access under CC BY 4.0.
DOI 10.1016/j.ijcrp.2026.200659
Figures from the article
O/E compares the heart attacks observed with those the model expected: 1 is perfect calibration.
External validation of the same model · not in this article
The same model, without retraining, was validated with US data. It is an analysis separate from the article: its figures do not come from it.
We process personal data under Colombia's Law 1581 of 2012.
 United StatesHealth data under the US standard
 European UnionPersonal data protection, EU standard
We comply with HIPAA (United States) and GDPR (European Union) to protect health data.

Chief Executive Officer
Leads the strategy, the relationship with institutional clients (payers, providers, insurers) and the commercial operation of Corpus AI.

Chief Operating Officer
Owns operational execution, the rollout with each client and the internal processes that sustain clinical delivery.

Tech Lead
Leads platform architecture, EHR integrations and the engineering discipline behind every prediction: idempotency, determinism, auditability.

Chief Medical Officer
Internist and clinical cardiologist in the heart failure program at Clínica Universitaria Colombia. MBA. Responsible for the model's clinical validity.

Chief AI Officer
PhD(c) in psychology applied to AI. Leads the development of the predictive model, calibration and validation. Lead author of the article published in IJCRP 2026.
“We have been in the cardiovascular fight for 80 years, and it frustrated me to see that we are losing it. That is why Corpus AI exists: we are here to show that a Latino's risk is not the same as that of a 1.90 m white European. A 1.60 m mestiza woman also deserves evidence-based medicine made to her measure. That is why we measure you against our own population.”
The physicians on our Advisory Board are with us throughout the process: they review what we do and watch over the model's clinical validity and its implementation in the care workflow.

Hospital Management · General Director · Fundación Santa Fe de Bogotá
General Director of Fundación Santa Fe de Bogotá. He brings the perspective of someone who runs a high-complexity hospital: how prediction gets implemented in real institutions without breaking the clinical workflow.

Cardiology · Public Health · Former Minister of Health of Colombia
Cardiologist and former Minister of Health of Colombia. He watches that the model makes sense at health-system scale: populations, insurance, and public prevention policy.

Critical Care · Intensive Care Medicine · Universidad El Bosque · Centro Policlínico del Olaya
Internal-medicine physician, intensivist, and Latin American reference in critical care. His clinical review keeps the model’s cohorts meaningful for patients who pass through the ICU.
Clinical data that already exists in the system: lab results, vital signs, diagnoses and medications. The published model was derived from routine clinical data in electronic health records. The data comes in through HL7, FHIR, CSV or files exported from the health record; Corpus structures and deduplicates it before calculating risk.
It depends on how available and complete the clinical data already in the organization's system is. The model is not retrained for each client: it is recalibrated to the local incidence, as the article recommends, and validated before the cohorts are turned on.
There is an external validation. The same model, without retraining, was validated in NIH All of Us with 626,396 US adults and obtained O/E ≈ 0.98. That validation is separate from the IJCRP 2026 article, which describes the model's derivation in 382,589 patients in Colombia.
We process personal data under Colombia's Law 1581 of 2012, and we comply with HIPAA (United States) and GDPR (European Union) to protect health data. The specific security measures and the terms of processing are set with each client in the implementation agreement.
Actionable cohorts, not a score. Each patient lands in one of four cohorts, with its clinical action, its time window and the modifiable factors that explain their risk. That way the team knows whom to escalate within 24 hours, whom to contact within 7 days, whom to give a care plan and whom to follow passively.
By events prevented and cost avoided against the client's baseline. In a real production deployment with a health-system partner in Latin America: 550+ acute cardiovascular events prevented, $2.3M USD saved and ↓20% monthly heart attack incidence. Name withheld for confidentiality.
30 minutes with our team. We look at your case.